Vaccines against human papillomavirus (HPV) do not warrant a general recommendation
This article ought to make every vaccinating doctor think twice about the HPV vaccine. In his matter-of-fact way, Michael Palmer manages in just a few paragraphs to pose the key fundamental questions about HPV vaccination so clearly that it must become obvious to anyone that the efficacy and safety of these injections are highly questionable.
Robert Cibis
By Prof. Dr. Michael Palmer
Once again, a campaign is currently underway to vaccinate children and young people against infection with human papillomavirus (HPV).1 But is this campaign really scientifically sound? This article sets out that there is no urgent need for such vaccination, and that the vaccines currently available have, moreover, not yet been shown to be either effective or safe. On the contrary: the limited data available on the safety of the vaccines gives cause for serious concern. A general recommendation cannot therefore be justified.
Preliminary remark
This overview is based on a more detailed, recently published report by the Croatian scientist Dr Lucija Tomljenovic 2 Dr Tomljenovic’s article also refers to more comprehensive reports written by herself and other experienced scientists. All these documents (in English) are freely available online, as is the majority of the literature to which they refer.
The virus
Human papillomaviruses belong to a family of DNA viruses. They primarily infect the skin and mucous membranes. These infections often manifest as warts. Skin warts are harmless; they may persist for a while, but usually disappear on their own once the immune system finally manages to fight them off. Warts on the mucous membranes can affect the genitals, the anus, and the mouth and throat. They are usually transmitted through intimate contact. These, too, often disappear spontaneously. In some cases, however, they not only persist but may also develop into cancer. This occurs most commonly in the cervix, but the other areas of the body mentioned above may also be affected. The likelihood of a simple infection developing into cancer depends heavily on the virus subtype. Among the subtypes associated with cancer, HPV-16 and HPV-18 are the most common in unvaccinated individuals. In people who have been vaccinated against these two subtypes, other subtypes occur relatively more frequently.
The purpose of vaccination
The stated aim of the HPV vaccination is cancer prevention, in particular the prevention of cervical cancer in women. An earlier vaccine, introduced in 2006, targeted only the above-mentioned subtypes 16 and 18. Vaccines are now in use that cover up to nine different subtypes of the virus. The vaccination is recommended in particular for children and young people before they become sexually active.
How effective is the vaccine in protecting against cancer?
Assessing the effectiveness of the cancer vaccine is not entirely straightforward, for the following reasons:
- the long latency period between infection and the development of cancer. Even if the vaccine were to prevent all infections with all cancer-causing HPV subtypes, a significant impact on cancer case numbers would only be expected after a delay of several years;
- the significant potential for statistical bias arising from variables such as participation in cancer screening programmes, which are remarkably effective in the case of cervical cancer.
Due to the long latency period of cancer, most studies on vaccine efficacy are based on other endpoints, i.e. on the infection itself or on cellular abnormalities that are not yet classified as cancer (‘cervical intraepithelial neoplasia’, conventionally referred to as dysplasia). It should be noted, however, that early-stage dysplasia can still resolve spontaneously, just like warts. Among the studies that have attempted to assess the prevention of ‘true’ invasive cancer, the one by Lei et al. from 2020 is the most optimistic.3 These authors analysed data from 1.6 million Swedish girls and women aged between 10 and 30. The analysis covered the period from 2006 to 2017. They concluded that the incidence of cancer was reduced by 88 per cent among those who had been vaccinated before the age of 17. A significantly more modest effect was reported in another study, which analysed the results of around 350,000 young women from Spain, England and Norway. Here, a reduction in dysplasia of around 40 per cent was observed following vaccination. The number of invasive cancer cases was too small for statistical analysis (fewer than 5 in total).4 It is entirely reasonable to assume that the vaccination would reduce the number of invasive cancers to a similar extent as it does dysplasia. However, this is not a foregone conclusion, as the detection of dysplasia during screening would be followed by treatment to prevent it from progressing to actual cancer. It should also be noted that the optimistic study by Lei et al. cited above did not take into account the participation of women and girls in such screening programmes. It stands to reason that women who opt for vaccination are also more likely to undergo screening. Such an effect could significantly skew the study’s results.
One approach that is unlikely to be susceptible to such bias is to compare different types of cervical cancer that can be distinguished histologically (i.e. through microscopic examination of tissue). The two most common types are known as squamous cell carcinoma and adenocarcinoma. In both cases, HPV is detected in the tumour tissue in more than 90 per cent of cases. However, there is also a ‘mixed group’ of rarer histological types, many of which are not associated with HPV. Whilst it is not entirely straightforward to determine the exact proportion of HPV-negative cases amongst these other forms, it is likely to be less than 50 per cent. Therefore, if the HPV vaccine were to protect against HPV-related cancer, the number of mostly HPV-positive adenocarcinomas and squamous cell carcinomas should decline more rapidly than that of the rarer, often HPV-negative variants. Consequently, the relative proportion of the rarer types in the total number should increase over time. However, this cannot be observed: Whilst the overall incidence of cervical cancer among young women in the USA has fallen remarkably sharply since 1999, the incidence of the rare types has declined even more rapidly, with their proportion falling by about half between 1999 and 2022 (Figure 1).
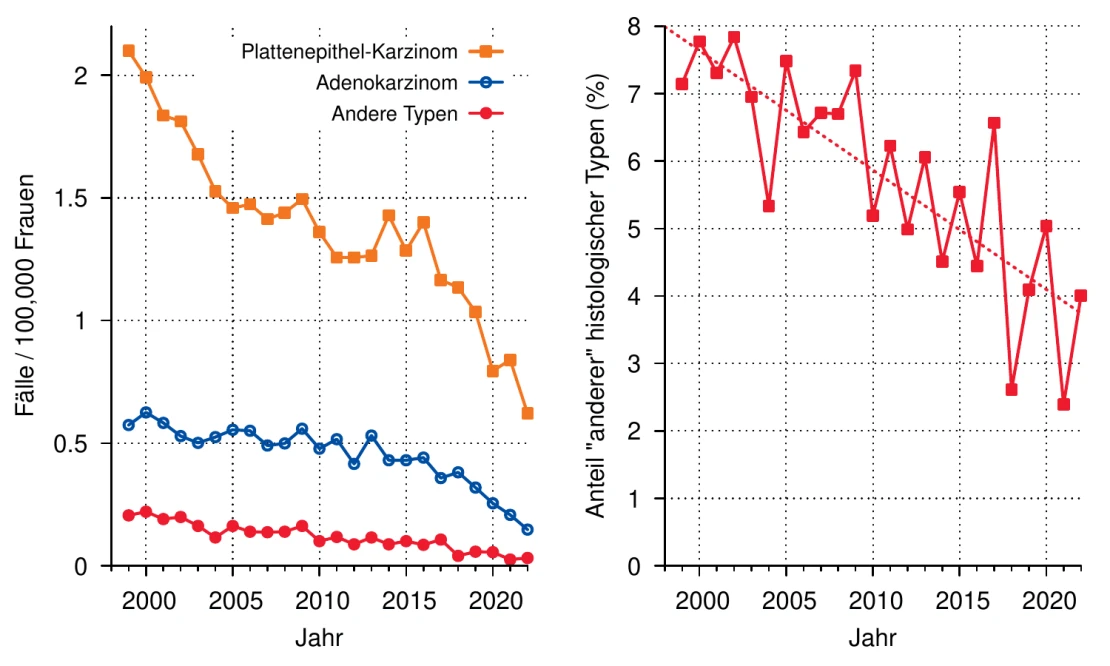
Figure 1: Incidence of cervical cancer in women aged 15–29 in the USA between 1999 and 2022, by histological type. Left: Data from Figure S2 of the study by Gopalani et al. (2026).5 Right: Proportion of rare histological types out of the total number of cervical carcinomas. The trend line is a linear regression.
Image source: Michael Palmer
What could be causing the remarkable overall decline in the incidence of cervical cancer? It is most likely due to increased screening. In line with this assumption, the incidence of HPV-related cancers for which no screening – namely penile, anal and oropharyngeal cancers – have remained at a constant level or even risen over recent decades. Where data are available, this also applies to young men; they are likely to be more likely to have received the HPV vaccination than older men. Admittedly, the available data are so limited overall that it cannot be conclusively established that the HPV vaccine has no preventive effect against these types of cancer. However, the opposite is equally true – as with cervical cancer, no preventive effect can be demonstrated here either.
What conclusions should we draw from the limited evidence on cancer prevention?
As there is currently no evidence that the HPV vaccine provides reliable protection against cervical cancer, it cannot replace regular cancer screening. Furthermore, such screening is effective and straightforward. It should be noted, in general, that all common HPV-related cancers occur in easily accessible parts of the body. Just like cervical cancer, cancers of the anus, oropharynx or penis could, in principle, be detected at an early stage through screening. If such screening is deemed unnecessary, then there is presumably no urgent need for a preventative vaccination either.
HPV vaccines
The HPV vaccines utilise an interesting technology known as ‘virus-like particles’. These synthetic particles resemble viruses in size and shape, and, just just like real viruses, they also carry a large number of antigenic protein molecules on their surface. Our immune system is designed to respond vigorously to natural viruses, and vaccines that mimic their structure also elicit a strong immune response. Unlike real viruses, however, these vaccine particles do not contain copies of the viral genome; they should not be confused with conventional live vaccines or with the adenovirus-, such as the toxic COVID-19 vaccines produced by AstraZeneca and Janssen.
Apart from the highly effective form of antigen presentation, HPV vaccines also contain a very potent aluminium-based adjuvant. This acts as a non-specific inflammatory stimulus. The inflammation triggered in this way further enhances the immune response to the antigen further. Overall, therefore, both the antigen preparation and the adjuvant are designed to elicit a strong immune response. Whilst this may seem positive at first glance, it also carries risks.
The risk of immunological cross-reactions
Our immune system has many powerful weapons at its disposal with which it can attack all kinds of microbes, including bacteria, fungi, parasites and viruses. To combat viruses, it also destroys cells in our own body that it recognises as being infected by a virus. These weapons must, of course, be handled with great care to avoid causing harm to ourselves. The immune system’s ability to distinguish between ‘self’ and ‘non-self’ is indeed remarkable. Nevertheless, mistakes can occur. Certain microbial antigens trigger immune responses that attack not only the microbe in question but also the body’s own molecules and cells. A well-known example is streptococcal infections of the throat or skin. Such infections are often self-limiting and can also be treated effectively with penicillin; in most cases, they resolve without any long-term consequences. In some patients, however, the infection is followed by a serious condition known as acute rheumatic fever. In this condition, the immune response triggered by the infection also targets the body’s own antigens in the heart, joints, kidneys or even the central nervous system. This leads to severe damage to these organs. Other examples include acute reactive arthritis, which is triggered by intestinal infections with Campylobacter or Yersinia bacteria, and Guillain–Barré syndrome, a serious disorder of the peripheral nervous system which can, for example, follow an infection with the Epstein-Barr virus.
The risk of such harmful cross-reactions is always largely determined by individual genetic characteristics, in particular by the combination of histocompatibility antigens in each person. These are precisely the same genetic markers that also determine the compatibility of organ transplants. You are probably aware that these antigens are highly variable. It is extremely unlikely that my neighbour and I would be well advised to donate bone marrow to one another. It is equally unlikely that we would be susceptible to exactly the same autoimmune diseases triggered by infectious agents. Exactly the same applies to autoimmune diseases triggered by vaccines. It follows that testing a new vaccine on a relatively small group of volunteers cannot reliably determine the risk of adverse events due to immunological cross-reactions. And there is another aspect to consider: natural pathogens have been present throughout human evolution; the most serious adverse reactions have therefore probably already been weeded out by natural selection. The same does not, however, apply to artificial antigen preparations, i.e. vaccines. Papillomaviruses are, of course, also ancient, but a natural infection with such a virus is confined to one or a few sites on the skin or a mucous membrane and, at best, triggers a muted immune response – as can be seen from the often long-lasting persistence of such infections. This cannot be compared with the systemic injection of a large quantity of papillomavirus antigen, combined with a potent adjuvant. The latter presents our immune system with a completely new challenge – with unpredictable risks.6
Can the HPV vaccine cause harmful cross-reactions?
Yes, it can. Whilst it is difficult to say exactly how often this occurs, the fact itself has been substantiated by a statistical analysis of reports collected by the US ‘Vaccine Adverse Event Reporting System’ (VAERS). To understand the basis of this analysis, we need to take a step back. The purpose of VAERS is to record suspected cases of adverse events occurring following vaccination. Whilst this is useful, it is subject to significant limitations:
- Not all incidents that occur are reported. The percentage of reported cases is likely to be in single figures;
- Some of the reported events may not actually have been caused by the vaccine in question, but may have occurred purely by chance shortly after vaccination.
We cannot, therefore, take the figures for such reports recorded by VAERS for a particular vaccine at face value. It stands to reason, however, that the proportion of purely coincidental reports should not depend on the vaccine in question. So if a specific event is reported more frequently following a particular vaccine than is the case on average for the other vaccines, then we can at least regard these excess reports as genuine and substantial.
Dr Tomljenovic carried out a thorough comparative study based on this principle. She found that certain adverse events were reported significantly more frequently following HPV vaccination than for all other vaccines combined (with the exception of COVID-19 vaccines; see Figure 2). Among these events, there is a strikingly high number of autoimmune diseases, e.g. lupus erythematosus, arthritis, multiple sclerosis and alopecia. Hormonal disorders and disorders of the autonomic nervous system are also more common, as are thromboses and embolisms. Further details can be found in the report cited in footnote 1. These findings provide strong evidence of a significant potential for immunological damage mechanisms.
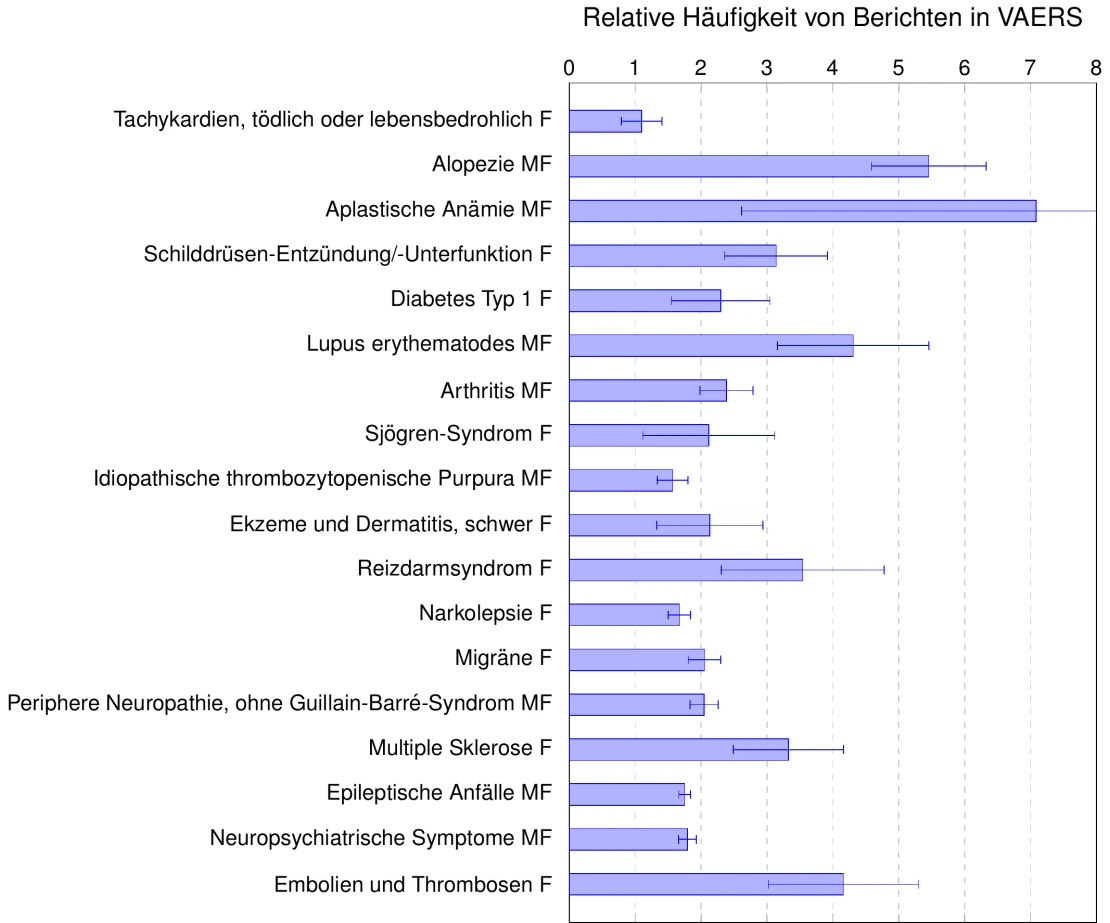
Figure 2: Selected results from the analysis of VAERS reports on HPV vaccination, covering the period 2006–March 2025, for male and female (MF) or female-only (F) vaccine recipients aged 6–29 years. The values along the X-axis indicate the factor by which the relevant disorder or condition is overrepresented in reports on HPV vaccines. Horizontal lines indicate the 95 per cent confidence intervals. The first condition listed (tachycardia) is not overrepresented ; it cannot therefore be considered to be substantiated by this analysis. All other conditions are statistically significantly overrepresented.
Image source: Michael Palmer
Conclusion
Whilst it is, in principle, plausible that HPV vaccines could reduce the incidence of cancers caused by HPV infections in the long term, this cannot be clearly demonstrated on the basis of the data currently available. This may be due to a latency period of several years latency period between infection and clinically detectable cancer. However, such a time lag also means that there is sufficient time to detect and treat cancer at a precancerous or early stage through regular screening. On the other hand, there is a serious risk of severe adverse reactions to the vaccine, even though this risk cannot be precisely quantified on the basis of the limited data available. Neither the benefits nor the risks can therefore currently be accurately assessed. On this basis, however, these vaccines cannot be recommended to the general public.
Sources and notes
- See, for example,https://www.bayern.de/gerlach-setzt-bei-der-krebspraevention-verstaerkt-auch-auf-hpv-schulimpfaktionen-bayerns-gesundheitsministerin-modellprojekte-in-rosenheim-und-aschaffenburg-sind-erfolgreich-verlaufen/ and https://www.mdr.de/nachrichten/deutschland/gesellschaft/hpv-impfung-
gebaermutterhalskrebs-100.html. ↩︎ - Tomljenovic, L. (2026) Public Comment: Human Papillomavirus Vaccine (HPV)
https://archive.org/details/tomljenovic-white-paper ↩︎ - Lei, J. et al. (2020) HPV Vaccination and the Risk of Invasive Cervical Cancer. N. Engl. J. Med. 383:1340–1348
http://dx.doi.org/10.1056/NEJMoa1917338 ↩︎ - Alcalde-Herraiz, M. et al. (2026) The effectiveness of HPV vaccination against invasive cervical cancer and related
precancerous lesions: a multinational target trial emulation study. Lancet Prim. Care 2:100114
http://dx.doi.org/10.1016/j.lanprc.2026.100114 ↩︎ - Gopalani, S.V. et al. (2026) Declines in cervical cancer incidence among young women in the United States. J. Natl. Cancer Inst. 118:941–946 https://www.ncbi.nlm.nih.gov/pubmed/?term=41883186 ↩︎
- The ‘most natural’ vaccine ever invented is probably the live polio vaccine, which mimics not only the natural pathogen itself but also its route of transmission. ↩︎
Never miss a show
New films, shows and articles by email – free, unsubscribe anytime.